
Septal motion
| View | PSAX at the papillary-muscle level for septal position and LVEI; A4C observed during respiration for interdependence; M-mode for timing. |
|---|---|
| Timing | Note when flattening occurs: end-diastole, end-systole, or both; note early-diastolic bounce and respiratory shift. |
| Caliper / trace | LVEI = LV anteroposterior / septolateral dimension at end-systole and end-diastole (1 = round). |
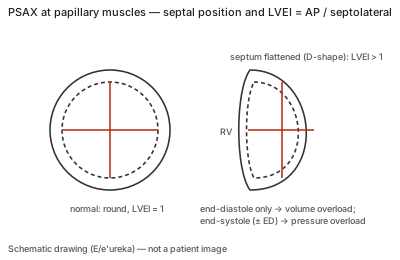
Correct example
Septal motion is described as normal (rightward), leftward, paradoxical, flattened or conduction-related, independently of wall scoring; flattening at end-diastole only suggests RV volume overload, at end-systole pressure overload, and at both pressure with or without volume overload.
Common error
Measuring LVEI on an oblique short axis, scoring post-operative, LBBB or paced septal motion as ischaemic, or failing to watch the septum through respiration when constriction is a question.
Effect on interpretation
The timing of flattening separates volume from pressure overload; an early-diastolic septal bounce with respiratory septal shift and IVC plethora is among the listed features of constriction, whereas conduction and post-surgical patterns are not loading abnormalities.
Why
The septum sits between two ventricles and bows away from the chamber with the higher pressure at each phase; LVEI quantifies that curvature, but it depends on an accurate plane and is confounded by pre-excitation, pacing, prior surgery and constriction.