
Chronic tricuspid regurgitation by Doppler echocardiography
Native valves
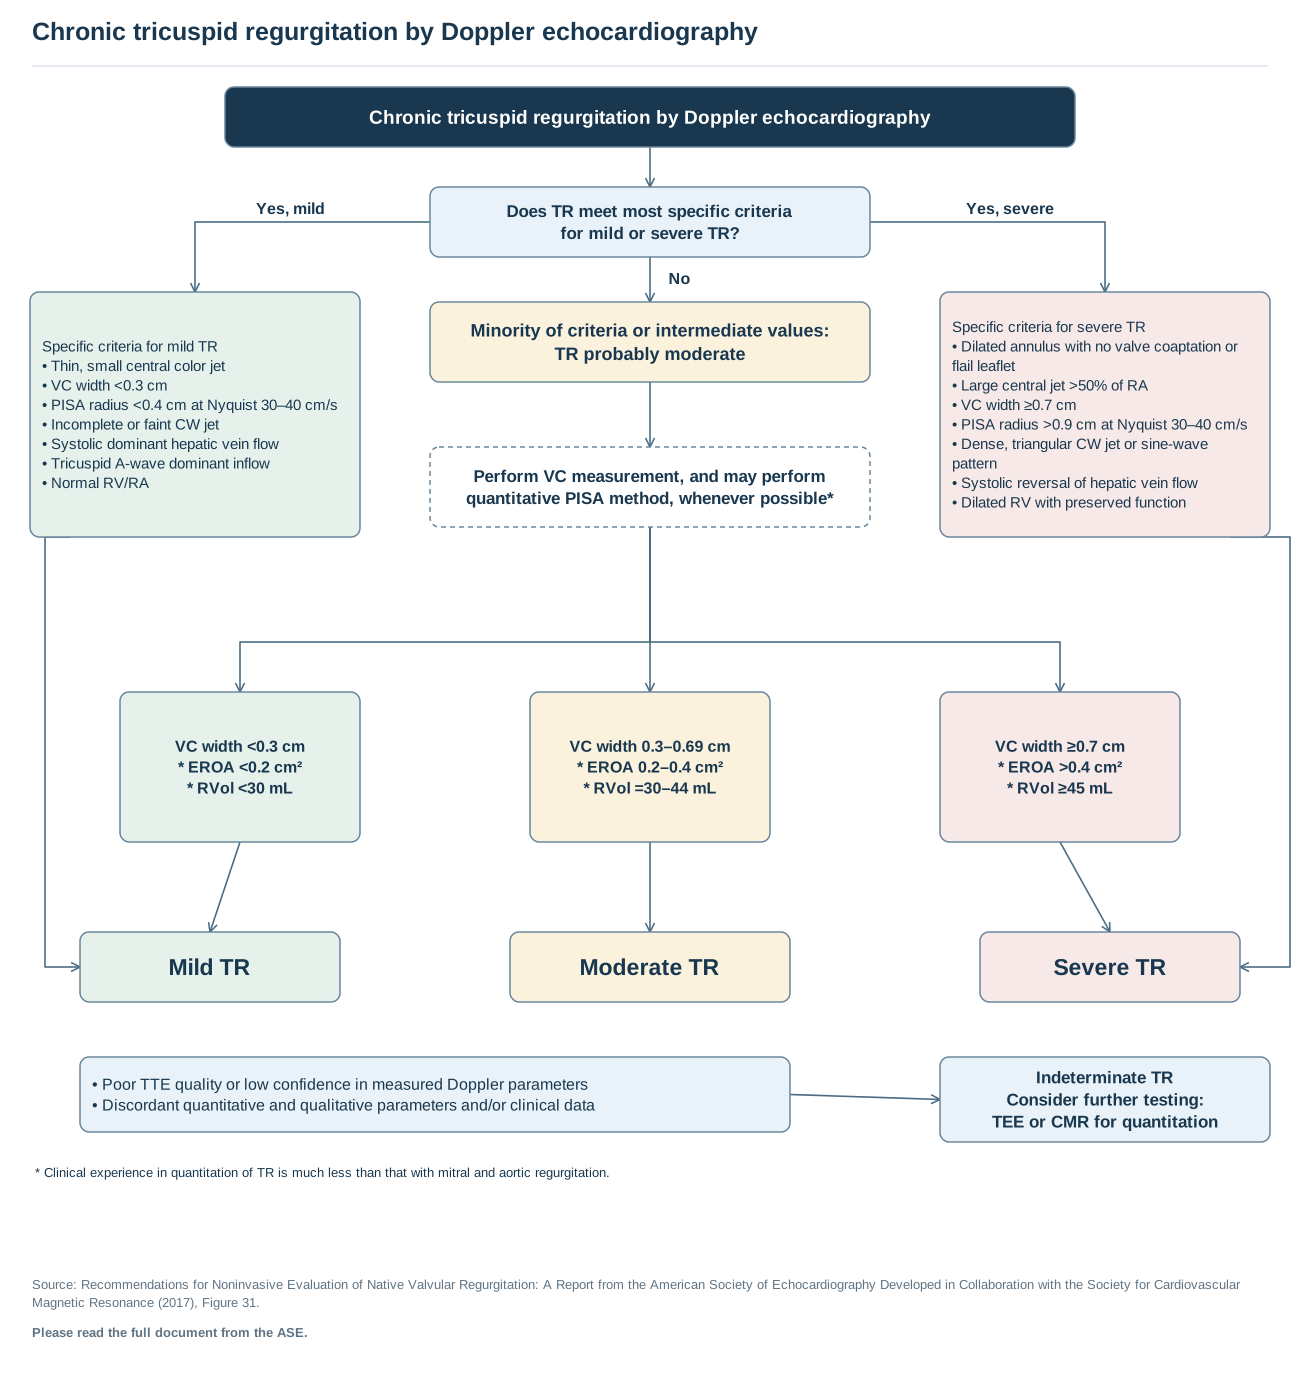
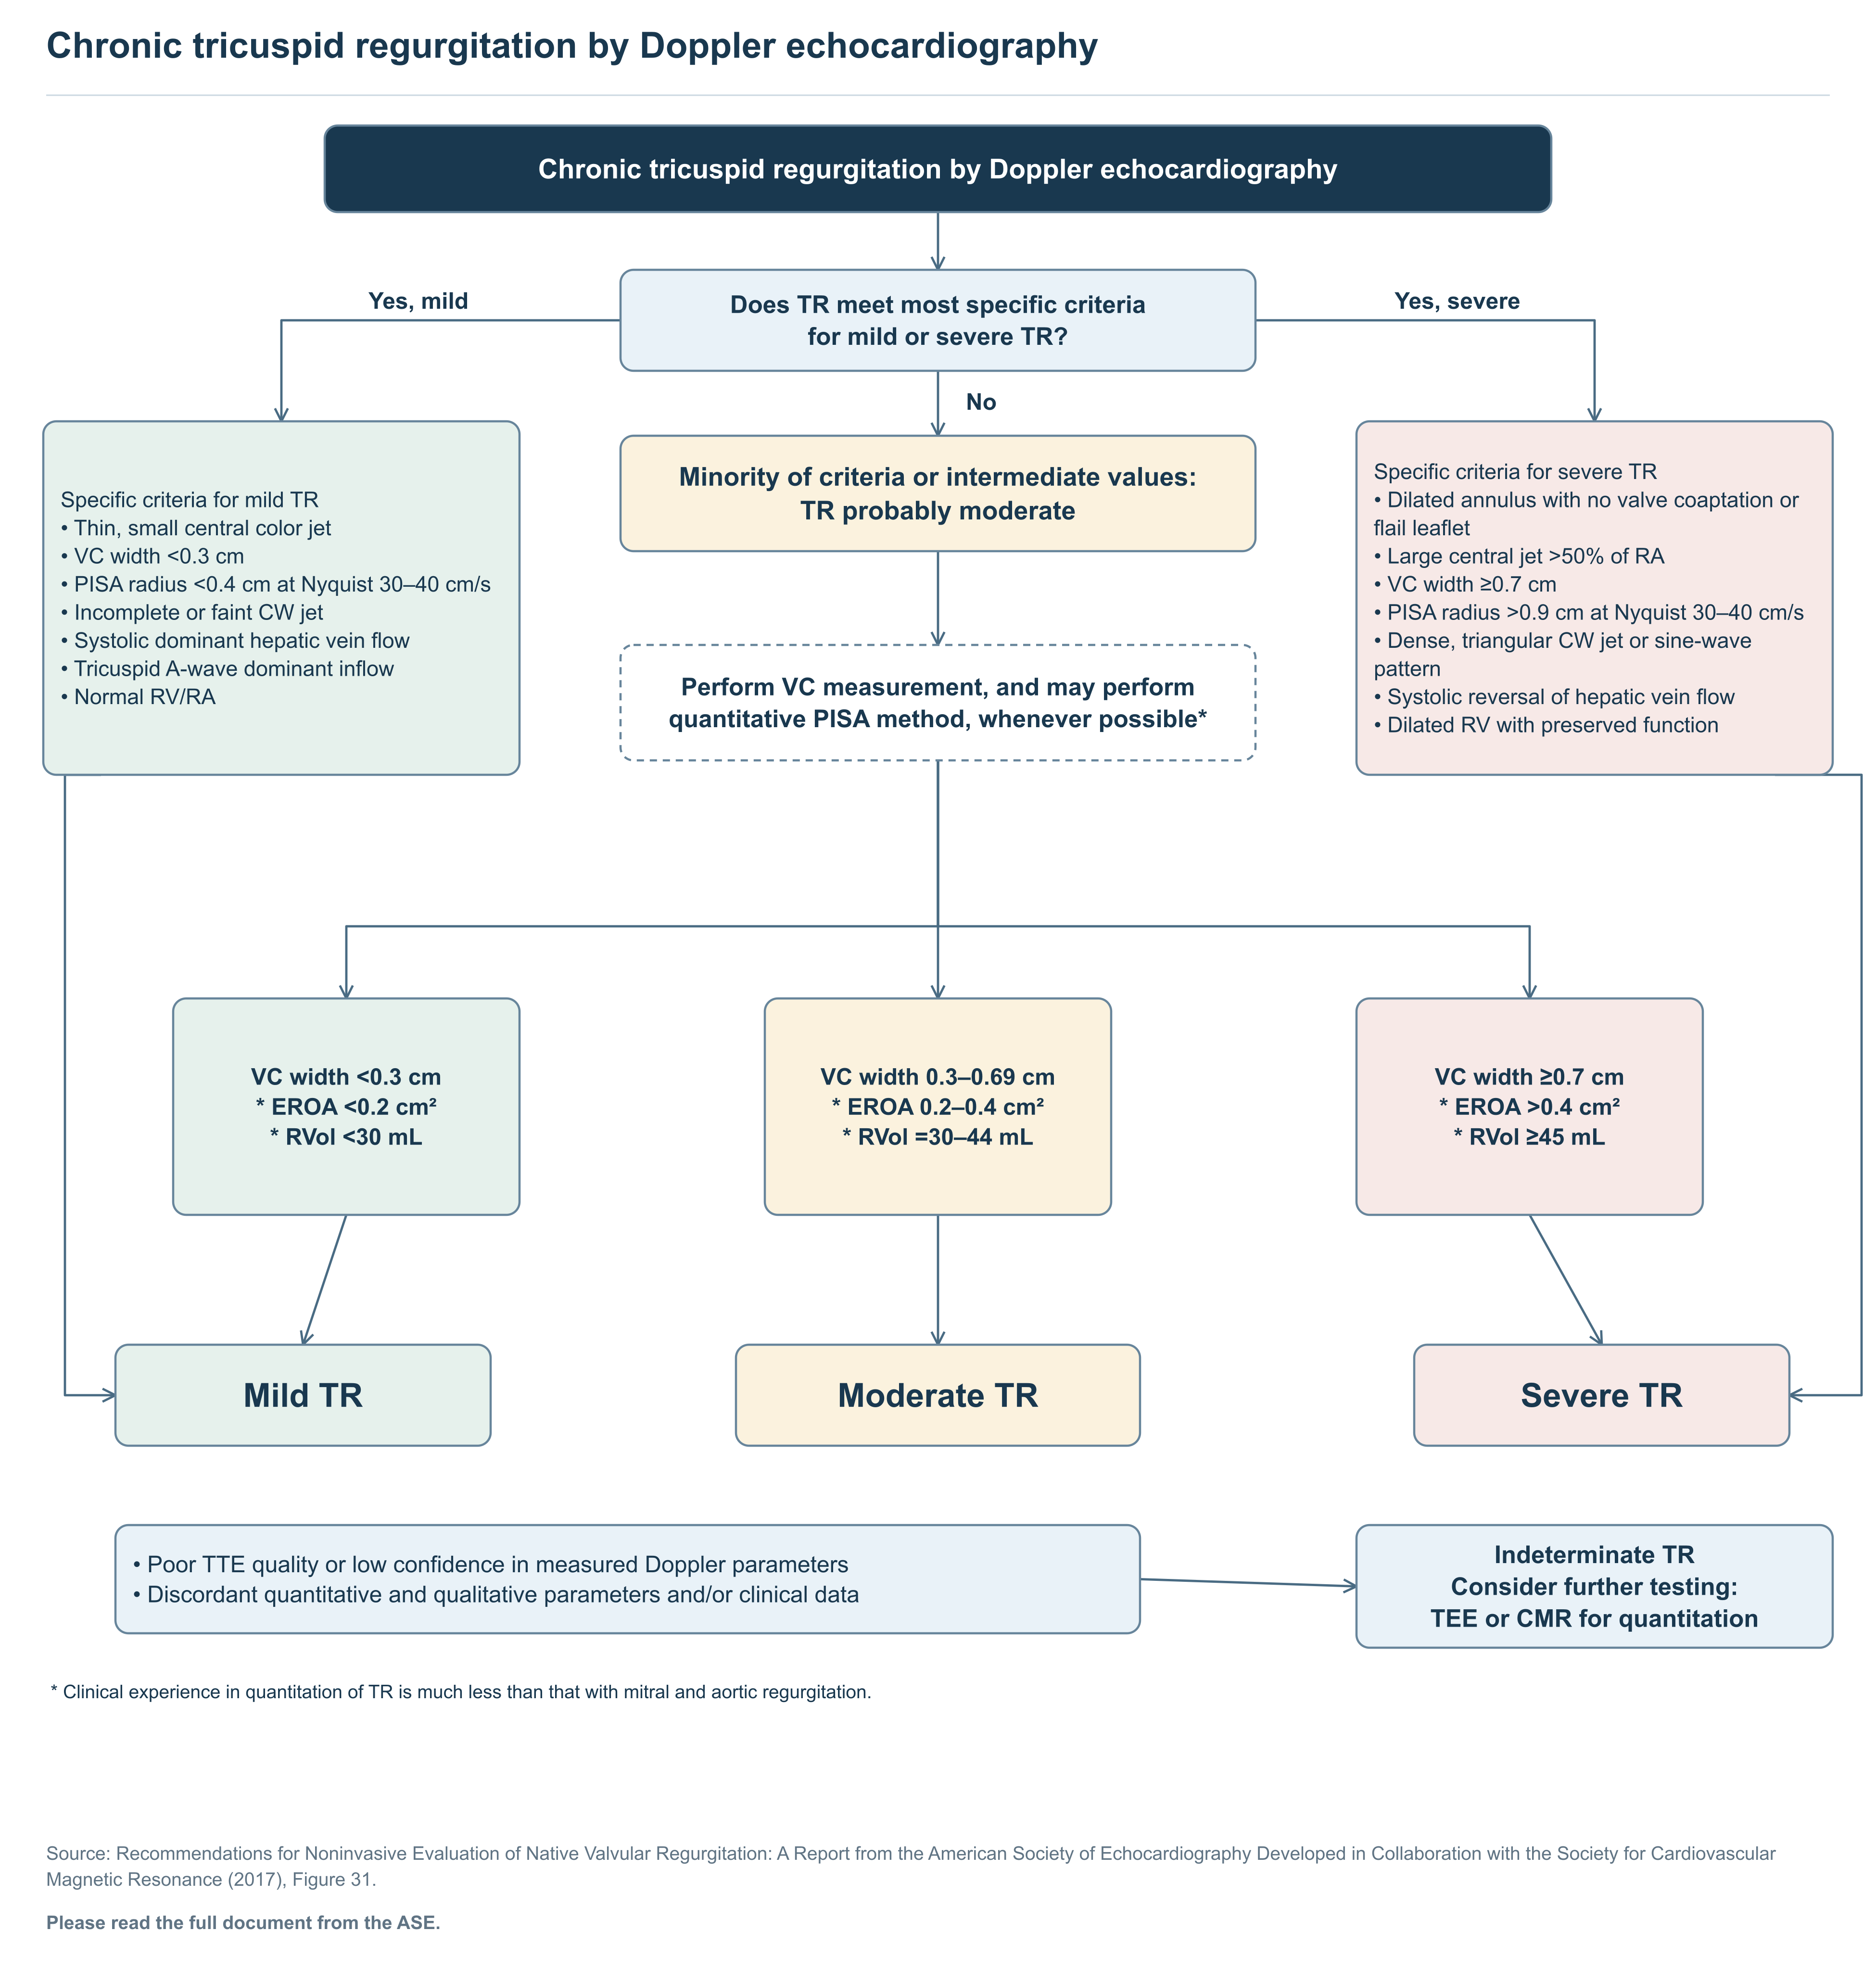
Text of this figure
- Chronic tricuspid regurgitation by Doppler echocardiography
- Yes, mild
- Yes, severe
- No
- Chronic tricuspid regurgitation by Doppler echocardiography
- Does TR meet most specific criteria
- for mild or severe TR?
- Specific criteria for mild TR
- • Thin, small central color jet
- • VC width <0.3 cm
- • PISA radius <0.4 cm at Nyquist 30–40 cm/s
- • Incomplete or faint CW jet
- • Systolic dominant hepatic vein flow
- • Tricuspid A-wave dominant inflow
- • Normal RV/RA
- Specific criteria for severe TR
- • Dilated annulus with no valve coaptation or
- flail leaflet
- • Large central jet >50% of RA
- • VC width ≥0.7 cm
- • PISA radius >0.9 cm at Nyquist 30–40 cm/s
- • Dense, triangular CW jet or sine-wave
- pattern
- • Systolic reversal of hepatic vein flow
- • Dilated RV with preserved function
- Minority of criteria or intermediate values:
- TR probably moderate
- Perform VC measurement, and may perform
- quantitative PISA method, whenever possible*
- VC width <0.3 cm
- * EROA <0.2 cm²
- * RVol <30 mL
- VC width 0.3–0.69 cm
- * EROA 0.2–0.4 cm²
- * RVol =30–44 mL
- VC width ≥0.7 cm
- * EROA >0.4 cm²
- * RVol ≥45 mL
- Mild TR
- Moderate TR
- Severe TR
- • Poor TTE quality or low confidence in measured Doppler parameters
- • Discordant quantitative and qualitative parameters and/or clinical data
- Indeterminate TR
- Consider further testing:
- TEE or CMR for quantitation
- * Clinical experience in quantitation of TR is much less than that with mitral and aortic regurgitation.
- Source: Recommendations for Noninvasive Evaluation of Native Valvular Regurgitation: A Report from the American Society of Echocardiography Developed in Collaboration with the Society for Cardiovascular
- Magnetic Resonance (2017), Figure 31.
- Please read the full document from the ASE.
Redrawn as a flowchart from the published document named in the figure. Read the full document for context and the figures' complete notes.